
Written and clinically reviewed by Louise Yow, Principal Physiotherapist & Director, AHPC A1300363H; hand, wrist and finger sections by Nigel Chua, Principal Hand Occupational Therapist & Director, AHPC A1300362Z.Last reviewed 6 October 2026.
Climbers are the most stubborn patients we see.
Not difficult. Stubborn in a very specific way. A runner with a sore knee stops running. A climber with a sore finger tapes it, drops a grade, and keeps climbing for another four months.
We understand why. Climbing is not really a workout. It is a social life, a problem to solve, a project you have been on for six weeks, and a group of people expecting you on Tuesday. Stopping costs more than the pain does.
So this article will not tell you to rest. It tells you exactly what is happening in your body, which parts of these injuries are slow to recover, and where the line actually sits between an injury you can train around and one you cannot.
Three of the five are hand and wrist injuries, which our hand therapists treat. The other two sit with our physios, and each one is marked.
Every climbing injury, by body part
Start from where it hurts. Each linked row goes to the page that covers that injury in full. Rows marked “see a doctor first” are not ours to treat first.
| Where | Injury | How climbing usually causes it |
|---|---|---|
| Hand and finger | Finger pulley tear | Crimping small holds, or a foot slip |
| Hand and finger | Trigger finger | High-volume crimping |
| Hand and finger | Lumbrical tear | Pocket holds with the fingers split |
| Hand and finger | Finger collateral ligament sprain | Side-loading in pockets and pinches |
| Hand and finger | Jammed finger (volar plate injury) | Crimp and pocket overload |
| Hand and finger | Finger joint pain and swelling (capsulitis) | Years of crimping |
| Hand and finger | Jersey finger (torn finger flexor tendon) | The feet cutting loose while hanging off a crimp |
| Wrist | TFCC tear | Underclings and sidepulls |
| Wrist | ECU tendon pain, little-finger side of the wrist | Slopers and underclings |
| Wrist | Scaphoid fracture | A bouldering fall onto the hand |
| Wrist | Wrist fracture | A fall from a boulder |
| Elbow and forearm | Brachialis strain (climber’s elbow) | Lock-offs on steep walls |
| Elbow and forearm | Golfer’s elbow (inner elbow) | Pulling volume |
| Elbow and forearm | Tennis elbow (outer elbow) | Slopers and pinches |
| Shoulder | SLAP (labral) tear | Dynamic moves and deadpoints |
| Shoulder | Rotator cuff tendon pain | Gastons and long overhead reaches |
| Shoulder | Shoulder dislocation or instability | Catching a dyno |
| Shoulder | Shoulder impingement | Overhead volume |
| Neck | Neck pain from a held posture | Looking up while belaying (belayer’s neck) |
| Thigh | Hamstring strain | Heel hooks |
| Knee | Meniscus tear | Drop-knees and heel hooks |
| Knee | MCL sprain | Drop-knees |
| Ankle | Ankle sprain | Landing between pads |
| Ankle | Ankle fracture | A bouldering fall |
| Ankle | Heel bone (calcaneus) fracture | Landing heel-first from height |
| Foot | Bunion pain | Tight climbing shoes |
| Foot | Big toe arthritis (hallux rigidus) | Years of toes curled in tight shoes |
The A2 Pulley Injury (Your Finger)
The one everybody has heard of and almost nobody understands correctly.
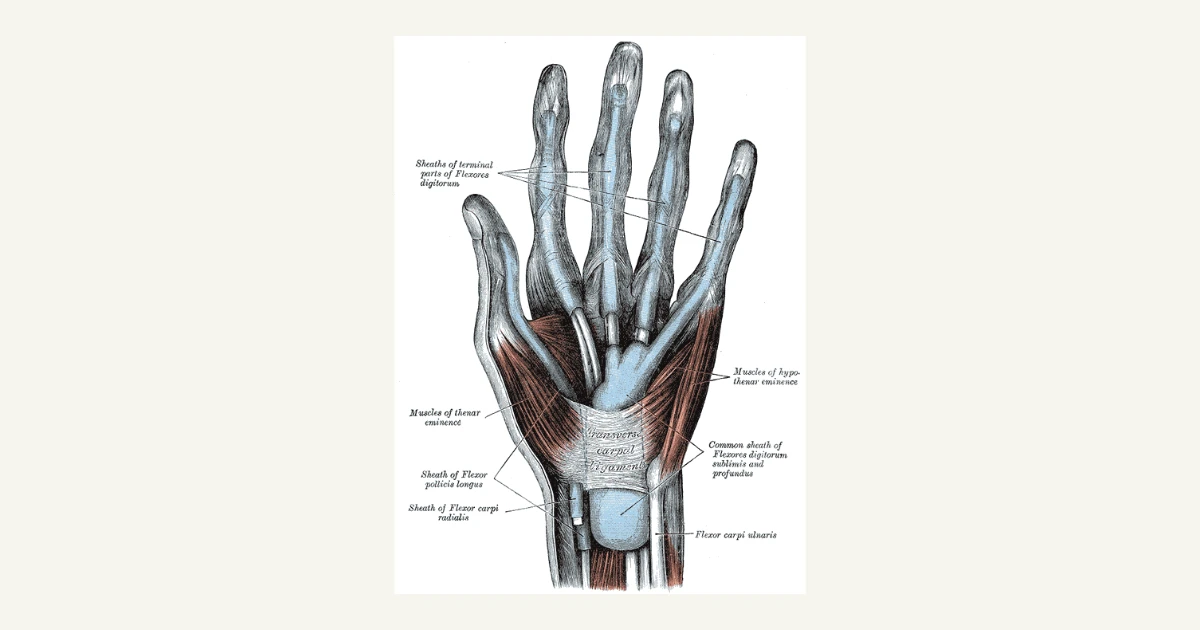
What it actually is. Your finger has no muscles. Tendons run from your forearm through the finger and pull it closed. Those tendons are held tight against the bone by a series of thin fibrous rings called pulleys. The biggest and most important one, called A2, sits over the first section of your finger.
When you crimp, especially a full crimp with the finger bent hard and the fingertip pressed down, the tendon tries to lift away from the bone. The pulley is the only thing stopping it. All of that force lands on a structure a few millimeters wide.
How you will know. Most people hear or feel a pop. Sharp pain at the front of the finger, near the base, on the palm side. Swelling comes in over the next day. Bending the finger against resistance hurts. In the worst cases, when several pulleys go at once, you can actually see the tendon lifting off the bone under the skin when you make a fist. That is called bowstringing and it is a surgical problem.
Where climbers go wrong. Two places.
First, they call it a tendon injury. It usually is not. The tendon is fine. The retaining ring failed. That distinction matters because tendons and pulleys heal on different timelines and respond to completely different loading.
Second, and this is the expensive one, pain settling down is not the same as the pulley healing. The pulley remodels and regains strength over months, not weeks. Around week four or five most people feel fine and go straight back to crimping. That is precisely when the structure is at its most vulnerable and precisely when the partial tear becomes a complete one.
What treatment actually looks like. Most pulley injuries do not need surgery. The graded strains and even many complete single pulley ruptures do well with the right program. Protection early, often with a thermoplastic ring worn over the injured section. Then a staged return where open hand and half crimp positions come back long before full crimp does. Hard crimping is usually the last thing to return, sometimes at the three month mark and beyond.
Multiple pulley ruptures with visible bowstringing are a surgical conversation, and we will refer you for one.
About taping. Tape does not prevent pulley injuries in any meaningful way. What it does do is give useful support during a controlled return to climbing. So use it as part of a plan, not as permission to keep loading something that is torn.
How pulley injuries are graded
Climbing pulley injuries are usually graded from I to IV. The grade is set by examination and scan, and it decides the plan:
| Grade | What it means | Usual path |
|---|---|---|
| I | A strained pulley | Managed with load changes and taping, and a gradual return to climbing |
| II | A partial tear of the A2 or A3 pulley, or a complete tear of the A4 | A protective ring splint and a staged return over weeks |
| III | A complete tear of the A2 or A3 pulley | A protective ring splint and a longer staged return, with the hard crimp last |
| IV | Several pulleys torn, or one torn with a muscle or ligament injury, often with bowstringing | A hand surgeon first, then rehabilitation after the repair |
The grading is from Schöffl and colleagues’ work on climbers’ pulley injuries.1
The lumbrical tear: pain in the palm on a pocket
The lumbricals are small muscles in the palm that start on the finger tendons. Pulling hard on a one- or two-finger pocket, with one finger bent hard and the finger next to it straight, pulls those muscles apart. It feels like pain deep in the palm, at the base of one finger, that gets worse when you straighten the neighboring finger while that one is bent. It is often mistaken for a pulley injury. The plan is different: buddy taping to keep the two fingers working together, and pockets brought back last.
Jersey finger: a fingertip that will not bend
If a finger was yanked straight while you were gripping hard, and now the fingertip will not bend on its own, the deep finger tendon may have pulled off the bone. It happens most often in the ring finger. See a doctor the same day. This is not a pulley injury, and it does not settle with rest. After a repair, rehabilitation follows the Flexor Tendon Repair Recovery Program.
1. Schöffl V, Hochholzer T, Winkelmann HP, Strecker W. Pulley injuries in rock climbers. Wilderness Environ Med. 2003;14(2):94-100.
The Swollen, Stiff Finger Joint
This is the injury nobody posts about, and the one we most want climbers to take seriously.
What it actually is. The middle joint of the finger gets loaded, twisted and compressed thousands of times per climbing day on small holds and pockets. The joint lining becomes irritated and thickened. The small ligaments on the sides of the joint get strained. Over time the joint itself starts laying down extra bone at the edges.
How you will know. The finger is puffy around the middle knuckle. It is stiff in the morning and takes a while to close fully. It aches after climbing rather than during. There is often no single moment where it went wrong, which is exactly why it gets ignored.
Where climbers go wrong. They accept it. Fat fingers get treated as a badge of the sport, the visible proof you actually climb. And for a while it is harmless.
Here is the part that is worth knowing. Long term climbers develop measurable joint changes in their fingers, and the ones who get there fastest are the ones who spent years climbing through chronically swollen, stiff joints without ever changing anything. Cartilage does not grow back. The thickening you can see on your finger is not decoration. It is the joint responding to more load than it can handle.
What treatment actually looks like. This is unglamorous and it works. Settling the swelling. Improving full straightening of the joint, because a joint that never fully straightens stiffens faster. Finding which grip positions and which board angles are driving it, then adjusting the volume rather than stopping the sport. Sometimes a small night orthosis to hold the joint out straight while you sleep.
The goal is not to make you climb less. It is to make sure you are still climbing at fifty.
Climber’s Elbow
What it actually is. Two different problems that get the same nickname.
The common one is pain on the inside of the elbow, at the bony bump. The muscles that close your fingers all originate there through one shared tendon. Every hard crimp pulls on that spot. Load it faster than it can adapt and the tendon becomes irritated and disorganized.
The other one sits slightly higher, in the front of the elbow, in the brachialis muscle. This is the lock off injury, the one that shows up after a stage of steep board climbing and big static moves. It feels deep and it responds to a different program.
How you will know. Inside elbow pain that is quiet at rest and loud on the first few pulls of the day. Painful to grip. Sore when you carry the shopping. It often creeps in over weeks after a training block or after starting a hangboard.
Where climbers go wrong. They stretch it and they rest it completely. Neither works well. Tendons that have been under too much load do not want zero load. They want the right load, applied in the right way, for long enough to remodel. Complete rest gives short term relief and a weaker tendon, which is why the pain comes straight back on the first climb after a two week break.
What treatment actually looks like. Our physios at Phoenix Rehab load these deliberately. Controlled, progressive, boring, effective. It takes weeks to months and it is measured by capacity rather than by how it feels on any given day. Most climbers keep climbing throughout, at a modified volume, which is usually what makes them willing to actually do it.
The Shoulder
What it actually is. The shoulder trades stability for range, which is what lets you reach a hold above and behind you. The price is that it depends heavily on muscular control rather than bone shape.
Climbers load it in the two positions it likes least. Overhead and pulling, repeatedly, thousands of times. Then suddenly, catching a dynamic move or a foot cutting loose, with the arm extended.
That produces rotator cuff pain, irritation of the tissue under the bony arch, and sometimes damage to the labral rim inside the joint, particularly after a sudden loading event with a clear before and after.
How you will know. Pain reaching overhead or across the body. A deep ache at the front or outside of the shoulder. Trouble sleeping on that side. In the sudden onset version, a specific move you can name and a shoulder that has not felt the same since.
Where climbers go wrong. Pulling more to fix it. Climbing is already an enormous pulling volume with very little pushing. The muscles that hold the shoulder blade in the right position get out muscled by the ones dragging it forward. Adding more pull ups to a shoulder problem is pouring petrol on it.
What treatment actually looks like. Our physios work out whether this is a control problem, a capacity problem, or actual structural damage, because those three need completely different plans. Most climbing shoulders are the first two and respond well. The sudden onset ones with a clear pop and a lasting change need proper assessment before anyone starts a strengthening program.
Ulnar Sided Wrist Pain (The Little Finger Side)
Back to the hand therapists, and the one most likely to be misdiagnosed.
What it actually is. On the little finger side of your wrist sits a small cartilage and ligament complex that lets the wrist rotate while still carrying load. Climbers hammer it. Mantling. Underclings. Any press out where the palm is down and the weight goes through a bent wrist. Slopers with the wrist rotated. Heel hooks where you are twisting your whole body around a loaded arm.
There is also a tendon that runs along that same side of the wrist and can become irritated or unstable, and the two problems feel almost identical from the outside.
How you will know. Pain on the pinky side of the wrist. Worse turning a door handle, pressing up out of a chair, or opening a jar. Sometimes a click or a clunk. Often no single incident, and often described as a sprain that never quite went away.
Where climbers go wrong. They wait. This is the injury we most often see six or nine months late, and the reason is always the same. It was called a sprain, they rested it, it improved slightly, they went back, and it settled into a low grade problem they stopped expecting to fix.
Some of these settle beautifully with the right load management and a period of protection. Some involve a tear that needs a surgical opinion. You cannot tell which one you have from a website, and the plan is different for each.
What treatment actually looks like. Proper assessment first, because ulnar sided wrist pain has a long list of possible causes and treating the wrong one wastes months. Then protection, staged loading, and a return to climbing that reintroduces mantling and rotation under load last rather than first.
The One Everybody Forgets: The Heel Hook Knee
Not in the top five, but it deserves a mention because it is the injury that ends seasons.
A hard heel hook puts your knee in deep flexion with the hip turned out and the whole body weight pulling through it. That is a brutal position for the cartilage discs inside the knee and for the hamstring where it attaches at the back.
If you felt something in your knee on a heel hook and it has been swelling or catching since, do not train around it. Get it looked at.
Bouldering falls: the injuries that come from landing
Bouldering has no rope, so every fall ends on the mat. Most falls are fine. The injuries come from landing on the edge of a pad or the gap between two, landing on straight legs, or reaching back with a straight arm to break the fall.
- Ankle. A roll on the edge of the mat. Most are sprains. If you cannot take four steps on it, or the back edge or tip of the ankle bone on either side, or the bone on the outer edge of the midfoot, is tender to press, see a doctor the same day to rule out a fracture. See ankle fracture.
- Heel. A drop from the top landing on the heels. Bruising is common. Go to the emergency department now if heel pain stops you standing after a high fall, especially if your back hurts too. A heel fracture from a fall can come with a fracture in the spine. See foot fracture.
- Wrist. Reaching back with a straight arm. Pain in the hollow at the base of the thumb after a fall on the hand can be a scaphoid fracture, even when the first X-ray is clear. See a doctor the same day. Once a doctor has confirmed it, see the Scaphoid Fracture Recovery Program and the Wrist Fracture Recovery Program.
- Shoulder. A fall onto an outstretched arm can dislocate it. If it looks out of place, go to the emergency department now, and do not let anyone pop it back in. See shoulder dislocation.
Call 995 after a fall onto the head or neck followed by confusion, neck pain with numbness, or weakness.
Land on both feet with the knees bent and roll back onto the mat. Keep the arms in.
Parkour: the same hands, harder landings
Parkour asks the hands for what climbing does, in cat leaps, wall runs and vaults, and adds drops onto concrete. The injuries follow that mix.
- Heels and ankles from drops and precision landings. The same rules as bouldering apply: if you cannot stand on it, see a doctor the same day.
- Achilles and the front of the knee from repeated jumps and landings. These are load problems, covered in Achilles tendinopathy and patellar tendinopathy.
- Wrists and fingers from vaults, rolls that go wrong and cat grabs on a wall edge. See finger sprain and wrist sprain. Hands are seen by our hand therapy team.
Traffic Light: Should You Be Climbing On This
| Green, train around it | Amber, get it assessed | Red, stop and get it seen |
|---|---|---|
| Mild ache after climbing that clears by next day | Pain lasting more than two weeks despite dropping grades | You heard or felt a pop |
| Soreness that warms up and improves | Swelling that keeps coming back | Visible bowstringing or deformity |
| No swelling, no loss of movement | Night pain or morning stiffness | Cannot fully bend or straighten the finger |
| Full grip strength on both hands | Pain that has started changing how you grip | Sudden loss of strength |
| Clicking or clunking in the wrist | Wrist or shoulder that gave way and has not recovered |
The amber column is where the money is. Almost every long, miserable, career limiting climbing injury we treat spent months sitting in that middle column being ignored.
What our patients say
Google reviews from our clinics in Singapore.


The Honest Summary
Climbers do not get injured because they are reckless.
They get injured because the sport lets you keep going. There is always an easier grade, a different wall, a way to grip that does not hurt as much. So the injury never forces the decision, and the decision never gets made.
The finger matters most, because fingers do not have spare capacity. You have ten of them and you use every one for the rest of your life. A shoulder can be rehabilitated for years. A joint that has already lost its cartilage cannot be given it back.
Get assessed early and the plan is usually small. Load management, a few weeks of protection, a staged return, and you keep climbing through most of it.
Getting It Looked At
Finger, hand and wrist injuries from climbing are seen by our hand therapy team, who assess whether a pulley is strained or torn, and whether wrist pain is a sprain or a cartilage tear, at the first appointment.
That is what decides your plan.
Tell us what you felt, which finger or joint, and how long ago. We will tell you honestly whether this is something to manage while you keep climbing, or something that needs a proper look before you touch a wall again.
One to one appointments at Orchard, Tampines, Serangoon and Tanjong Pagar, and at Jurong East from 25 October 2026.
You did not get into climbing to be careful. You got into it to move well, pull hard, and still be doing this in twenty years. That last part is the one worth protecting.
Frequently Asked Questions
I heard a pop in my finger while climbing. Is it serious? An audible pop with pain at the front of the finger near the base is the classic presentation of a pulley injury. Most are treatable without surgery, but the plan depends entirely on how much of the pulley failed. Get it assessed rather than guessing.
How long before I can climb again after a pulley injury? Easy climbing on open hand grips often returns within a few weeks. Full crimping is usually the last thing to come back and can take around three months. The timeline is set by the tissue, not by how the finger feels, which is why so many climbers reinjure at the six week mark.
Why are my fingers swollen after bouldering? Repeated compression and twisting irritates the lining of the finger joints. Occasional puffiness after a hard day on the wall is common. Swelling that never fully settles, or a joint that has become permanently thicker, means the load has been exceeding what the joint can handle for a long time.
Does taping prevent climbing finger injuries? Not meaningfully. Tape gives some support during a controlled return to climbing after an injury, but it does not protect a healthy pulley from a bad crimp. Treat it as a rehab tool, not as protective equipment.
Can I keep climbing with an injured finger? Sometimes, at reduced volume and on modified grip positions. It depends on the structure involved and the grade of injury. Climbing through a partial pulley tear on full crimp is the single most reliable way to turn a six week problem into a six month one.
What is climber’s elbow and how do I fix it? Pain on the inside of the elbow from the shared tendon of the finger flexors, or in the front of the elbow from the brachialis muscle after heavy locking off. Complete rest tends to fail. Progressive loading, guided properly, is what rebuilds tendon capacity.
Why does the pinky side of my wrist hurt when I mantle? That side of the wrist carries a small cartilage and ligament complex that takes heavy load when the wrist is bent back and rotated. Pain there is commonly labeled a sprain and commonly is not one. It is worth a proper assessment, because some of these involve a tear.
Should I stop climbing completely while I recover? Usually not. Total rest deconditions the tissue and rarely holds up when you return. The better approach for most climbing injuries is a modified plan that keeps you on the wall while removing the specific position or grip that is driving the problem.
When should I see a hand therapist instead of waiting it out? If you heard a pop, if there is swelling that keeps returning, if a finger will not fully straighten or bend, if pain has lasted more than two weeks despite dropping grades, or if you have lost grip strength. Any of those is worth an appointment.
Do climbing injuries cause arthritis later? Long term climbers do show more joint changes in the fingers than non climbers. The risk is highest in people who trained hard for years through chronically swollen and stiff joints. Managing the load early is what protects the joint later.
Climbing: what we focus on
The finger that popped on the crimp.
A pop at the base of a finger on a hard crimp. A middle joint that has been fat and stiff for months. The shoulder that felt loose on a big move. Climbers are good at training through pain, which is the problem.
- Finger pulleys and joints. Assessed and splinted by our hand therapy team. A finger joint that stays fat and stiff: the Stiff Finger Joint Recovery Program.
- Elbow. Golfer’s elbow and tennis elbow, loaded back progressively.
- Shoulder. Instability after a big move: the Shoulder Dislocation and Labral Repair Recovery Program.
Tested, not dated. You go back when the measures say so: grip and finger strength against the other hand, and hangboard load introduced in stages. Pain is the first thing to leave. Strength is the last to train and recover.
WhatsApp us · Get Assessed & Treated · One 45-minute appointment, $230, nett, no GST.
Where are you with this right now?
1. It is settling on its own
Most injuries and most flare-ups settle over weeks with sensible load management and a return to normal movement. Improvement is judged over a month, not over a day, and good days and bad days inside that are usual. If you are doing more this month than last, and sleeping better, it is behaving the way it should. You do not need us for this, and we would rather say so.
2. It has stopped improving
You have adapted without noticing. The other side takes the load, you plan movements you used to make without thinking, and you have quietly dropped things you used to do.
Pain is the first thing to leave. Movement and strength are the last things trained back, and most people stop before that part is done. That is the gap worth measuring, and it is not measured by how you feel on the day.
The Stalled Recovery Review is three appointments over three weeks with the same therapist, because what a joint does under load cannot be read in one visit. The first finds what is limiting it. The next two measure how it responds. $690, nett, no GST, which is three appointments at $230.
3. You have had surgery, or you have a date
Recovery after an operation has a shape, and knowing which stage you are in tells you whether you are on it. See the recovery programs, hand and physiotherapy, or the four stages and what each one works on if you are not sure which applies to you.
All of it runs on the same four stages. The Phoenix Recovery Protocol explains what each stage works on and what you have to meet to move up. No referral needed to start.
Next step
Find out which stage you are in
Pain is the first thing to leave. Movement and strength are the last things trained back, and most people stop before that part is done. One Assessment and Treatment is a single 45-minute appointment at $230, nett, no GST. Your therapist finds what is actually limiting you, treats it in the same appointment, and you leave with your current stage and a written plan.
Prefer to phone? Each of our five clinics has its own number on the clinics page. No referral needed to book.
Related reading
Where we are
Clinics across Singapore
ORCHARD
400 Orchard Road #12-12
Orchard Towers, S238875
NS22 Orchard MRT
Physiotherapy and hand therapy in Orchard →
WhatsApp 8800 1830TAMPINES
9 Tampines Grande #01-20
Asia Green, S528735
EW2DT32 Tampines MRT
Physiotherapy and hand therapy in Tampines →
WhatsApp 8780 9608SERANGOON
265 Serangoon Central Drive #04-269
S550265 · Lift C only
NE12CC13 Serangoon MRT
Physiotherapy and hand therapy in Serangoon →
WhatsApp 8892 4121TANJONG PAGAR
10 Anson Road #02-77A
International Plaza, S079903
EW15 Tanjong Pagar MRT
Physiotherapy and hand therapy in Tanjong Pagar →
WhatsApp 8227 7074JURONG EAST
2 Venture Drive #02-02
Vision Exchange, S608526
NS1EW24 Jurong East MRT
Opening 25 October 2026
Physiotherapy and hand therapy in Jurong East →
WhatsApp 8242 7340