
Written by Zita Sham, Fairuuz Saleh and Shiv Mohan Banka, Principal Physiotherapists at Phoenix Rehab.Clinically reviewed by Louise Yow, Principal Physiotherapist & Director, AHPC A1300363H.Last reviewed 9 October 2026.
You roll onto that side at two in the morning and wake up. That is usually the first thing people with a rotator cuff problem tell us. Not the badminton smash that started it. The sleep.
Then the small things stack up. Reaching back for the seatbelt. Pulling a shirt off over your head. Drying your back with a towel. None of it is dramatic. All of it is a reminder.
Most people wait. They rest it two weeks, feel better, go back to the court, and it returns a little worse. Six months later they are still working around it and wondering whether the shoulder is just like this now.
What matters is knowing which kind you have. A worn, irritated tendon and a fresh tear in a 40 year old who came off a bike are not the same problem and do not get the same plan. Most of these shoulders do well without an operation. Some need a surgeon soon.
What the rotator cuff actually is
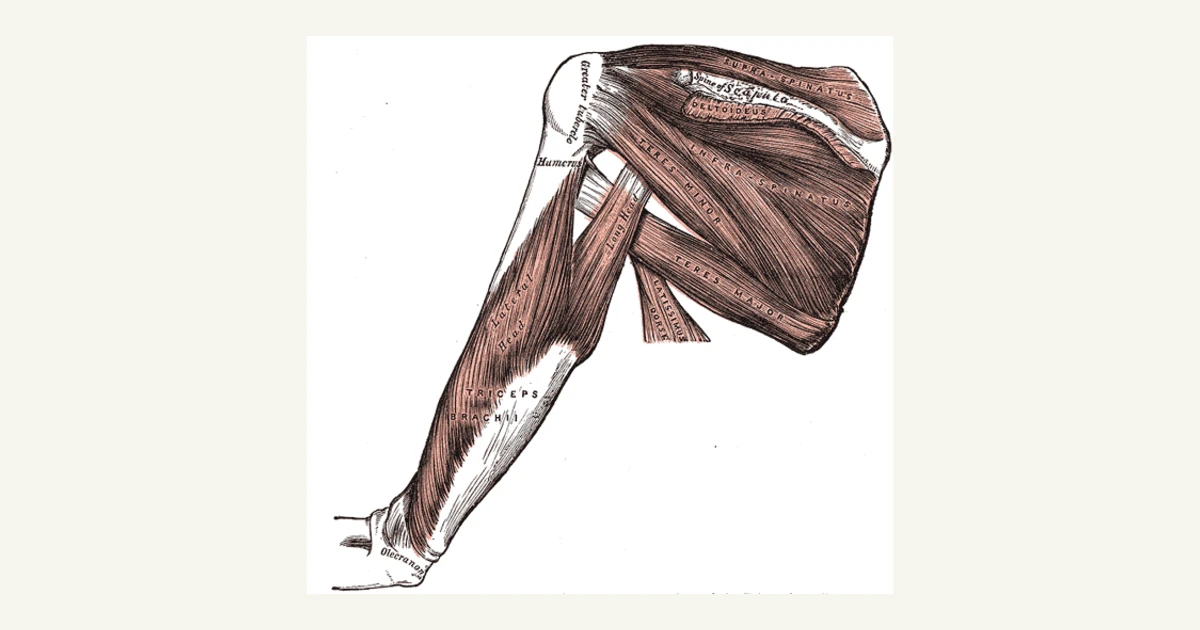
The rotator cuff is not one muscle. It is four, sitting deep, wrapped around the top of your upper arm bone.
- Supraspinatus runs across the top of the shoulder. This is the one that gets irritated or torn most often.
- Infraspinatus sits behind, on the shoulder blade, and turns the arm outwards.
- Teres minor sits below it and helps with the same job.
- Subscapularis is on the front, between the shoulder blade and the ribs, and turns the arm inwards.
Now the part that explains everything else. Your shoulder is a ball on a very shallow socket. Closer to a golf ball on a tee than to a hip, which is a proper ball in a proper cup. That is why it moves in more directions than any other joint you own, and why it needs constant help to stay centred.
The cuff is that help. The four muscles fire in small amounts, all the time, holding the ball pressed into the middle of the socket while the big muscles swing the arm. Steering and engine. The cuff steers.
When it works, there is clean space above the ball for the tendon to glide. When the cuff is irritated, torn or tired, the ball drifts up by a few millimeters during exactly the movements that need the most control. Overhead. Reaching in front. Rotating behind your back. In a space that small, that is the difference between gliding and grinding.
That one mechanism explains the pattern. Why it hurts overhead and not by your side. Why it hurts at night. Why you can be strong in most directions and oddly weak in one.
How to tell if this is what you have
Nobody diagnoses their own shoulder from a website. This is here to help you recognize a pattern and decide whether to get it looked at.
The classic picture
- Pain on the outside of the upper arm, often a band around the deltoid, rather than pinpoint on the joint.
- It bites when you reach overhead, out to the side, or behind your back.
- Night pain lying on that side. Many people end up on their back, or with a pillow under the arm.
- Getting a jacket on and off is annoying. Doing up a bra, or reaching a back pocket, is worse.
- Carrying a heavy bag straight down by your side is usually fine. That catches people out.
Pain that stops you, versus weakness that is real
Pain inhibition feels like the arm could do it, but your body will not let you. You lift, it catches sharply, and the arm stalls. Let the pain settle a few days and the strength comes back.
True weakness feels different. The arm simply does not go. No sharp catch. You lift and it drifts back down, or you cannot hold it up once someone places it there. Weakness still present on a good, low pain day is the finding that changes a plan, because it points to structural rotator cuff damage rather than an irritated tendon.
That is what our physios are testing for. Not whether it hurts. Whether it works.
What it gets confused with
Frozen shoulder. With a cuff problem you keep most of your movement, it just hurts at the end. With a truly frozen shoulder the range is gone in every direction, including when someone else moves the arm. If you are losing range rather than strength, read the page on frozen shoulder.
Neck referral. The neck throws pain into the shoulder and upper arm convincingly. Clues include pain that changes when you turn your head, pins and needles, or numbness. Cuff pain almost never goes past the elbow. If yours does, look at neck pain and cervical radiculopathy.
What causes it
The slow one
Tendons age. From roughly the fourth decade the supraspinatus loses some of its blood supply and some of its tolerance for load. Add repeated overhead work and it becomes an irritated, overloaded tendon, which clinicians call tendinopathy. Over more years some of those tendons develop small tears from the inside out with no injury behind them. No fall. No moment. It became sore and stayed sore.
What loads it up in Singapore:
- Badminton. Two hours of overhead smashes, often straight after a full day at a desk with no warm up worth the name.
- Swimming. Thousands of rotations a swim in a condo lap pool. Freestyle and butterfly.
- Overhead pressing in the gym. Barbell and dumbbell press, plus behind the neck pressing and wide grip pulldowns behind the head.
- Desk work. Nine hours with the shoulders rolled forward and the blades parked in one position. That does not injure a cuff by itself. It leaves the muscles that control the shoulder blade slow and weak, so when you do play, the cuff does a job it was never meant to do alone.
- Work lifting. Retail, food and beverage, logistics, anything with repeated reaching above chest height.
The fast one
A fall onto an outstretched arm. Catching yourself on a railing. Lifting something heavy at a bad angle and feeling a sudden tear with immediate weakness. A motorcycle or PMD accident. A dislocation.
Under about 55, with a sudden event followed by genuine weakness, that is a different conversation with a clock on it.
When you need to get this looked at
Most shoulder pain is not an emergency. Some of it is time sensitive. This is where that line sits.
Get seen by a doctor the same day if:
- A fall, dislocation or sudden heavy strain was followed by real weakness, especially if you cannot lift the arm out to the side or hold it there.
- The arm feels dead, or gave way suddenly and has not come back.
- You have numbness, pins and needles or weakness in the hand or fingers.
- The shoulder looks deformed, or you cannot move it at all after an injury.
- There is fever, redness, heat and severe pain in the joint.
- Unexplained weight loss, or unrelenting night pain regardless of position, alongside new shoulder pain.
The trajectory rule. The signal is not whether your shoulder hurts today. It is the direction it is heading. Pain slowly improving over two to three weeks is usually on the right track. Pain the same or worse after three to four weeks, or flaring every time you return to sport, will not resolve on its own. That is the point to get assessed. Not six months later when you have stopped playing.
Why the scan is more confusing than people expect
Plenty of people walk around with rotator cuff changes on an MRI and no shoulder pain at all, and the proportion climbs with age.
That is not a criticism of imaging or of any doctor who ordered one. Scans are useful, sometimes essential, particularly when surgery is being considered. The point is narrower. A scan shows the state of the tissue. On its own it cannot tell you whether that finding is why your shoulder hurts, because the same finding sits quietly in shoulders that feel fine.
So a report reading “partial thickness supraspinatus tear with tendinosis” is one piece of information. What it means for you depends on your age, how this started, and what the shoulder can do when someone tests it.
What happens if you leave it
A straight answer rather than a scare.
An irritated tendon without a tear will often calm down once the load comes off and then gets rebuilt sensibly. What it will not do is fix itself while you keep playing twice a week and pressing overhead. It settles into a low grade ache that flares whenever you push.
A degenerative tear is where waiting has a real cost. Most do not become disasters. Many people manage them well for years with good strength and sensible loading, and never need an operation. But a proportion slowly enlarge. As a tear gets bigger the torn tendon end can pull back towards the shoulder blade, which clinicians call retraction. A retracted tendon, with muscle that has started to waste, does not repair as reliably as a smaller tear caught earlier.
Not every tear marches towards surgery. But there is a window in which repair, if it is ever needed, works better than it does later, and you cannot see where you sit in it without being assessed.
An acute full thickness tear in a younger, active person is the time sensitive one. A healthy 42 year old who falls, cannot lift the arm, and has a tendon torn through deserves a surgical opinion soon rather than eventually. Not because someone will definitely operate, but because that decision has a clock on it and belongs to the surgeon.
Meanwhile the rest of you adapts. You hitch the shoulder blade up to get the arm moving. The neck gets involved. That becomes its own problem to unwind.
If your shoulder has been sore for more than a month and is not clearly improving, a WhatsApp to 8336 6009 saves a lot of guessing.
How it gets treated
From least to most invasive.
Changing what you load it with
Not rest. Almost nobody gets better by putting the arm in a sling and waiting, and complete rest makes these shoulders stiffer and weaker.
What helps is temporarily removing the positions provoking it, usually repeated overhead work and end range reaching, while keeping everything else moving. For most people that means pausing smashes and overhead pressing for a few weeks. Not pausing exercise.
Sleep matters too. A pillow hugged to the chest, or a folded towel under the upper arm when lying on the good side, often turns a broken night into a decent one.
Physiotherapy
For most degenerative and overload presentations this is the first line, and most orthopedic surgeons in Singapore will say the same before they discuss an operation.
Mechanically it does three things. Improve the cuff’s ability to hold the ball centred under load. Improve shoulder blade control, because a blade that does not rotate and tilt properly leaves the cuff working in a smaller space. Then rebuild the tendon’s capacity until it handles what your sport asks of it.
That last part is what people skip. A tendon sore for months has lost capacity. You cannot stretch capacity back. You load it back, progressively, and that takes a plan. Appointments with our physios at Phoenix Rehab find which part of that chain is failing and load it in the right order. The physiotherapy assessment is what makes the program yours rather than a handout.
Medication and injections
A corticosteroid injection into the space above the cuff can reduce pain substantially, sometimes for weeks or months. Used honestly it is a window. It buys enough comfort to do the rehabilitation that changes the shoulder. Used as the whole treatment it disappoints, because the pain returns and nothing underneath has changed. Platelet rich plasma injection comes up often too, and it is worth knowing what the evidence supports before spending on it.
Surgery
Some shoulders need repairing. An acute full thickness tear in a younger active person. A large tear with real weakness that has not responded to loading. A tear alongside other damage after a dislocation.
The surgeon decides whether to operate, what to repair, and how to fix it. Phoenix does the part that comes after, and it is longer than almost anyone expects. Repaired tendon is stitched to bone and needs time to knit before it takes load, which is why post-operative rehabilitation runs to protocol rather than to how you feel. A sling for several weeks. Someone else moving your arm before you move it yourself. Active movement without resistance before strengthening. Strengthening well before anything overhead. Many protocols do not clear return to sport until four to six months.
The people who do worst felt fine at week six and decided they were ahead of schedule. A repair that fails because it was loaded early is a far harder problem than the original tear.
After rotator cuff surgery
Rotator Cuff Repair Recovery Program
The repair is done in an afternoon. The tendon takes about three months to grow back onto the bone, and the shoulder starts to stiffen long before that.
In a rotator cuff repair, the surgeon stitches the torn tendon back onto the top of the arm bone, usually through keyhole incisions. The stitches hold it in place for now. The tendon still has to grow back onto the bone, and until it does, the repair is at its weakest. That is why the first weeks run to your surgeon’s protocol, not to how the shoulder feels. This program is run by our physiotherapy team and follows that protocol, stage by stage.
Bring your operation note. It says how big the tear was and how it was fixed, and those two facts set the pace more than anything else.
No referral needed. Every first visit is one 45-minute Assessment & Treatment, $230, nett, no GST.
Where are you right now?
- The operation is booked. Sort out sleep and clothes before the day: a recliner or a stack of pillows, shirts that button down the front, and a plan for the first weeks one-handed. An appointment before surgery lets your therapist measure the shoulder and teach you the early exercises while you still have both hands.
- You are in the sling. The nights are usually the hardest part of the first month. Your shoulder is moved for you, within the limits your surgeon set, while the elbow, wrist and hand are worked every day.
- The sling is off and the arm will not lift. That is expected at first. The question is whether range is coming back week on week, measured in degrees, not whether it feels better.
- Months on, and the top shelf is still out of reach. Read if it is not going to plan below.
What happens, week by week
The weeks below are the common shape after repair of a small to medium tear. Larger tears are usually protected for longer. Your surgeon’s protocol takes precedence over anything on this page.
- Weeks 0 to 6Stage 1 · Calm & ProtectSling for four to six weeks, as your surgeon instructs. Pain and sleep managed. The shoulder moved within your surgeon’s limits, while the elbow, wrist, hand and shoulder blade are worked every day.
- Weeks 6 to 12Stage 2 · Move & MobilizeOut of the sling. Assisted movement first, then lifting the arm yourself, without weights. Range measured in degrees at every review.
- Weeks 12 to 16Stage 3 · Rebuild & StrengthenRotator cuff and shoulder blade strength, loaded in small steps once your surgeon allows resistance. Strength measured against the other arm.
- Month 4 onwardStage 4 · Return & PerformOverhead reach, lifting, work tasks and sport. Many protocols do not clear overhead sport until four to six months.
The weeks are typical ranges, not a promise. You move up a stage when you meet its criteria, and your surgeon’s protocol takes precedence over anything on this page.
Is this normal after a rotator cuff repair?
Usually expected
- A numb, heavy arm for the first day while the nerve block wears off.
- Night pain, and sleeping better propped up than lying flat, for the first four to six weeks.
- Bruising that tracks down the arm toward the elbow.
- Puffy fingers and a stiff hand from the sling, which ease with daily hand and wrist movement.
- A shoulder that will not lift on its own when the sling comes off.
Contact your doctor
- Call 995 for chest pain or sudden breathlessness.
- Go to the emergency department now if pain is severe and getting worse despite painkillers, or the hand turns pale, cold or numb after the nerve block has worn off.
- See a doctor the same day for fever, a wound that is red, hot, opening or leaking, or a painful, swollen arm or calf.
- See your surgeon soon if you felt a pop or a sudden pain and the arm has lost strength it had, especially after week six. That is your surgeon’s question before more therapy.
Four months after a rotator cuff repair and still cannot reach the top shelf? What that usually means
The mug in the top cupboard goes to the other hand now, without you thinking about it. You hitch the shoulder up to get a shirt over your head. At the last review the surgeon looked at the scar and said it was healing well.
The usual plan at this point is to keep using the arm and wait for the rest to come back. Most of a normal day happens below shoulder height, so daily life never asks the repaired cuff to hold the arm up there. The pain is mostly gone. Has anyone measured how strongly that arm turns out, against the other one?
Range in degrees and rotation strength against your other arm are the two numbers that show where it stalled. A shoulder that only lifts by hitching the blade has a strength and control problem, and that gets trained, not waited out. Arrive at your next surgeon review with those numbers. If the strength dropped suddenly after a pop, that is your surgeon’s question first.
The Stalled Recovery Review is three appointments over three weeks with the same therapist, because how a repaired tendon responds to load cannot be read in one visit. $690, nett, no GST.
When can I…
Your surgeon decides, based on the size of the tear and the repair. These are typical points, not permissions.
| Activity | Typical point | What has to be true first |
|---|---|---|
| Desk work and typing with the other hand | 1 to 2 weeks | Pain controlled, and the sling on as instructed. |
| Sleep lying flat | Varies | Many people sleep propped up for the first four to six weeks. |
| Drive | 6 to 8 weeks or later | Out of the sling, your surgeon’s clearance, and able to turn the wheel hard with both hands. Check your insurer. |
| Light tasks at waist height | 6 to 8 weeks | Out of the sling, and Stage 2 has started. |
| Reach overhead without weight | 10 to 12 weeks | Lifting the arm without hitching the shoulder blade. |
| Swimming, badminton, overhead gym work | 4 to 6 months or later | Stage 4 criteria met, and your surgeon’s clearance. |
| Medical certificate | Your doctor issues it | Physiotherapists do not issue MCs. We can write a report on your functional limits for your doctor or employer. |
The four stages, and what moves you up
- Stage 1, Calm & Protect. The repair protected exactly as your surgeon instructed, sleep and pain managed, and every joint that is allowed to move kept moving.
Move up when: your surgeon allows the sling off and active movement, you sleep through most of the night, and elbow, wrist and hand range are full. - Stage 2, Move & Mobilize. Assisted, then active lifting and turning, measured in degrees at every review.
Move up when: you lift the arm to shoulder height and above without hitching the shoulder blade, range is recorded against the other arm, and your surgeon allows resistance. - Stage 3, Rebuild & Strengthen. Rotator cuff and shoulder blade strength, loaded in small steps and counted.
Move up when: rotation strength, measured on both arms, is approaching the other side, and you can hold the arm overhead without pain or a hitch. - Stage 4, Return & Perform. The overhead reach, lifting, work and sport you named at the first appointment, rehearsed and tested.
Graduate when: those tasks are tested and done, your surgeon has cleared you for sport where that applies, and a home program is in place to keep the strength.
Measured at your first appointment and again at graduation: shoulder range in degrees on both arms, rotation strength on both arms with a handheld dynamometer once your surgeon allows resistance, and a shoulder pain and function questionnaire (SPADI).
The physiotherapy team that runs this program
You are matched to the therapist whose declared clinical interest fits your shoulder and the clinic that suits you, and you stay with the same therapist through the program. Every appointment is one to one with your therapist for the full 45 minutes. All are registered with the Allied Health Professions Council.

Principal Physiotherapist. Achilles tendinopathy, rotator cuff injury and repair, shoulder stiffness.
Orchard, Tampines, Jurong East

Principal Physiotherapist. Shoulder and knee problems, spinal dysfunction, sports injury.
Orchard, Tampines

Principal Physiotherapist. Knee and hip replacement recovery, neck and shoulder pain, dry needling.
Tanjong Pagar, Jurong East

The program belongs to Phoenix, not to one therapist. Your plan, your measurements and your surgeon’s protocol move with you if you change clinic.
$230 per 45-minute appointment, nett, no GST
One to one with your therapist for the whole 45 minutes. Same price for your first appointment and your last. The Rotator Cuff Repair Recovery Program is set at 12 appointments across Stages 1 to 4, $2,760 in all. Your therapist confirms your plan at your first visit, and you pay for each appointment as you attend it.
This program runs Stages 1 to 4 of the Phoenix Recovery Protocol, and sits under physiotherapy after surgery alongside the rest of our recovery programs.
Twelve weeks after the repair and the arm still stops at your shoulder? Get Assessed & Treated, and leave knowing which stage you are in.
Phoebe, our WhatsApp assistant, replies with a clinic and two appointment times. Bring your operation note, your surgeon’s rehabilitation protocol if you were given one, and your sling.
Timeframes in this program are typical ranges, not promises. Where your surgeon has given you a protocol, that protocol takes precedence over anything written here.
Rotator cuff exercises and what to do at home
Read this first. These are general rotator cuff exercises for an irritated or mildly damaged cuff. They are not right for every shoulder, and they are wrong in the early weeks after a repair, where your surgeon’s protocol overrides everything here. If you have real weakness after an injury, get assessed first.
The pain rule. Some discomfort is fine. Up to about three or four out of ten, where ten is the worst pain you can imagine, settling back to baseline within a day. Sharp catching pain, pain that climbs as you continue, or a shoulder clearly worse next morning means back off the load or range. That is information, not failure.
1. Isometric external rotation at a doorframe. Stand beside a doorframe, elbow bent to ninety degrees and tucked against your ribs, the back of your wrist on the frame. Press outwards without moving, at about half effort. Hold 30 to 45 seconds, rest 30, repeat 5 times, daily. This loads the tendon without moving through the painful range, and often takes the edge off for hours.
2. Banded external rotation, elbow tucked. Light band at elbow height. Elbow at ninety degrees, a rolled towel squeezed between elbow and ribs. Rotate the forearm outwards about 45 degrees, slowly, and return slower than you went out. 3 sets of 12 to 15, three times a week. If the towel drops, the band is too heavy.
3. Scapular setting and rows. Band or cable at chest height. Before you pull, draw the shoulder blade back and down, then row the elbow towards your ribs. The pull comes from the blade, not from shrugging. 3 sets of 10 to 12, three times a week. Desk workers need this most and skip it most.
4. Prone Y and T. Lie face down with your arm hanging off the side of a bed. With no weight, lift the arm out at about 45 degrees from your head for a Y, thumb up, then lower slowly. Then straight out to the side for a T. 2 sets of 10 each, three times a week. Add half a kilogram once 10 clean repetitions feel easy with no flare next day.
5. Progressive loading. Once a movement stops challenging you it stops changing the tendon. Add a little load or range every week or two, one thing at a time, and judge it by how the shoulder feels next morning rather than during the set.
The setback nearly everyone gives themselves is overhead loading too early. Pressing, smashes, butterfly, pull ups. The shoulder feels better at four weeks, the Tuesday game goes ahead, and they are back where they started. Earn overhead. Rotation strength and blade control first, then partial range, then full.
What recovery actually looks like
Stages, not promises. Every shoulder runs on its own clock.
Weeks 0 to 3. Pain and sleep are the targets. Load comes off the provoking positions, isometrics go in, movement continues everywhere that does not hurt. Night pain usually eases first.
Weeks 3 to 8. Rotation strength and shoulder blade control get built. Seatbelts, jackets and reaching a shelf usually stop being a thought.
Weeks 8 to 16. Loading gets heavier and starts going overhead. Gym work returns with attention to what sits above shoulder height. Sport specific work begins near the end of this window.
Beyond four months. Full return to overhead sport for those who need it. Some are back sooner. Some take longer, particularly if the shoulder was sore a year before anyone looked at it.
What makes it slower: waiting months to start, diabetes, smoking, a larger tear, age, and stopping the program the moment the pain goes. That last one accounts for a lot of the shoulders that come back twice.
Getting assessed at Phoenix Rehab
A first appointment is mostly about working out which shoulder problem you actually have. Our physios ask how it started, what it stops you doing, and what your nights look like. Then they test it. Range in every direction, strength tested in ways that separate real weakness from pain, shoulder blade control, and the neck, because the neck refers here often enough that skipping it is careless.
You leave knowing what is most likely going on, whether it needs a scan or a doctor’s opinion, and what the first three weeks look like. If the examination suggests a full thickness tear that warrants a surgical opinion, we say so and help you get in front of an orthopedic surgeon quickly.
Shoulders are seen at our Orchard, Tampines, Serangoon and Tanjong Pagar branches, with Jurong East opening on 25 October 2026. Details are on the clinics page.
Frequently asked questions
How do I know if I have rotator cuff damage or just a strained shoulder? The clearest clue is weakness separate from pain. A strain hurts, then settles over a week or two. Rotator cuff damage often leaves the arm genuinely weak in one direction, usually lifting out to the side, even on a low pain day. Weakness still there after three weeks needs examining.
Can a rotator cuff tear heal on its own? A torn tendon does not knit itself back together the way a bruise fades. What can change is the pain and the function around it, and that often improves a great deal. Many people with degenerative tears get back to everything they want without surgery.
Do rotator cuff exercises make it worse? At the right load, no. Discomfort up to about three or four out of ten during the exercise, settling within a day, is expected. Sharp pain, or a shoulder clearly worse the next morning, means the load or range was too much. Adjust rather than stop.
Why does my shoulder hurt so much more at night? Lying on that side squeezes the small space above the cuff tendon where the irritation already sits. Nothing distracts you at night either, and irritated tissue is more sensitive after you have been still. Sleeping on your back, or with a pillow supporting the arm, helps most people.
Do I need an MRI for my shoulder? Not always. A scan matters most when surgery is being considered, when there was a clear injury with weakness, or when a shoulder is not responding as expected. Cuff changes show up in plenty of people with no pain at all, so the image gets read alongside an examination.
How long before I can play badminton again? For an irritated cuff without a tear, often around two to three months before full smashing, with lighter play back earlier. After a repair it is longer and follows your surgeon’s protocol. Do not test it with a full game. Return to the court in stages.
Is surgery the only real fix for a rotator cuff tear? No. Most degenerative tears are managed well without an operation. Surgery is right for a specific group, mainly acute full thickness tears in younger active people and larger tears with real weakness that have not responded to loading. The surgeon makes that call.
Get the shoulder looked at properly
If this has been going on more than a few weeks, or you are quietly changing how you sleep, reach and train to work around it, that is reason enough to get it assessed. You do not need to wait until you cannot lift the arm.
WhatsApp us on 8336 6009 . Tell us what it stops you doing and we work from there.
The point of all this was never a pain score. It is the reach for the top shelf you stop thinking about. The smash you can still hit at 55. Sleeping on whichever side you feel like. Carrying your own bags through an airport in twenty years. Shoulders looked after early tend to keep doing all of that.
Anatomic and reverse shoulder replacements rehabilitate almost oppositely, and which one you had decides the first six weeks. See the Shoulder Replacement Recovery Program, which sets out the four stages and what moves you up.
Kipping and overhead lifting in CrossFit, and the wall balls at the end of a HYROX race, both load the rotator cuff overhead. See CrossFit injuries and HYROX injuries. Dragon boat paddlers load the cuff on every reach and catch, covered in the dragon boat and paddling injuries guide.
Also on this site: the page on easing shoulder pain covers what helps and what does not.
Where are you with this right now?
1. It is settling on its own
Many shoulder problems settle over weeks to months. Night pain that slowly becomes less frequent, and reach that slowly returns, are the usual pattern. If you are reaching higher this month than last, and sleeping better, it is on the normal course. You do not need us for this, and we would rather say so.
2. It has stopped improving
You put your shirt on that arm first. The top shelf belongs to someone else now. You have stopped reaching behind you without thinking.
Reach comes back before strength does. A shoulder that goes overhead but cannot hold anything there is halfway, not finished. That is the gap worth measuring, and it is not measured by how you feel on the day.
The Stalled Recovery Review is three appointments over three weeks with the same therapist, because what a joint does under load cannot be read in one visit. The first finds what is limiting it. The next two measure how it responds. $690, nett, no GST, which is three appointments at $230.
3. You have had surgery, or you have a date
Recovery after an operation has a shape, and knowing which stage you are in tells you whether you are on it. See the Rotator Cuff Repair Recovery Program, or shoulder physiotherapy if you are not sure which applies to you.
All of it runs on the same four stages. The Phoenix Recovery Protocol explains what each stage works on and what you have to meet to move up. No referral needed to start.
Next step
Find out which stage you are in
Pain is the first thing to leave. Movement and strength are the last things trained back, and most people stop before that part is done. One Assessment and Treatment is a single 45-minute appointment at $230, nett, no GST. Your therapist finds what is actually limiting you, treats it in the same appointment, and you leave with your current stage and a written plan.
Prefer to phone? Each of our five clinics has its own number on the clinics page. No referral needed to book.
Related reading
- physiotherapy after surgery
- shoulder physiotherapy
- Shoulder Pain Diagnosis Chart: Understanding Common Patterns
- Shoulder Nerve Pain: Causes and What to Do
- Shoulder Blade Pain Relief: Options to Consider
- The Phoenix Recovery Protocol, and the four stages
- All recovery programs, hand and physio
- Frozen Shoulder: Why It Hurts Most At Night, And What Actually Helps
- Biceps tendonitis
Where we are
Clinics across Singapore
ORCHARD
400 Orchard Road #12-12
Orchard Towers, S238875
NS22 Orchard MRT
Physiotherapy and hand therapy in Orchard →
WhatsApp 8800 1830TAMPINES
9 Tampines Grande #01-20
Asia Green, S528735
EW2DT32 Tampines MRT
Physiotherapy and hand therapy in Tampines →
WhatsApp 8780 9608SERANGOON
265 Serangoon Central Drive #04-269
S550265 · Lift C only
NE12CC13 Serangoon MRT
Physiotherapy and hand therapy in Serangoon →
WhatsApp 8892 4121TANJONG PAGAR
10 Anson Road #02-77A
International Plaza, S079903
EW15 Tanjong Pagar MRT
Physiotherapy and hand therapy in Tanjong Pagar →
WhatsApp 8227 7074JURONG EAST
2 Venture Drive #02-02
Vision Exchange, S608526
NS1EW24 Jurong East MRT
Opening 25 October 2026
Physiotherapy and hand therapy in Jurong East →
WhatsApp 8242 7340What our patients say
Google reviews from our clinics in Singapore.


