
Written by Zita Sham, Fairuuz Saleh and Shiv Mohan Banka, Principal Physiotherapists at Phoenix Rehab.Clinically reviewed by Louise Yow, Principal Physiotherapist & Director, AHPC A1300363H.Last reviewed 13 October 2026.
Heel pain is most often plantar fasciitis: sharp pain under the heel on the first steps out of bed. Pain at the back of the heel points to where the Achilles attaches. A deep, bruise-like central ache suggests the fat pad. Impact pain in a heel sore to squeeze can be a stress fracture. Burning or tingling suggests a nerve.
Key takeaways
- Where it hurts is the first clue. Sharp pain under the heel on the first steps out of bed is usually plantar heel pain, often called plantar fasciitis.
- Pain at the back of the heel usually comes from the Achilles tendon where it joins the heel bone, or from a bursa or a bony bump just above it.
- Heel spurs are common in people with no heel pain at all, and heel pain routinely settles while the spur stays where it is.
- Heel pain is rarely a sign of cancer. Pain at night or at rest, fever, weight loss you cannot explain, or pain in both heels with stiffness in the back or other joints goes to a doctor first.
- Plantar heel pain is slow. Most people improve substantially, and it takes months rather than weeks.
What causes heel pain? Start with where it hurts
Heel pain is not one thing, and the wrong label leads to months of the wrong treatment. Press around your heel, notice when it hurts most, and find your row.
| Where it hurts | What it feels like | Most likely cause | First step |
|---|---|---|---|
| Under the heel, at the front inner edge where the arch begins | Sharp or stabbing on the first steps out of bed and after sitting. Eases after a few minutes of walking | Plantar heel pain (plantar fasciitis) | Cut the long standing blocks, wear supportive shoes indoors, and start calf and plantar fascia loading |
| Under the heel, with a spur on the X-ray report | The same as plantar fasciitis | Heel spur, usually alongside plantar heel pain | Treat the tissue. Spurs are common in people with no heel pain at all |
| The middle of the heel pad, under the bone | A deep bruise. Worse barefoot on hard floors and later in the day | Heel fat pad syndrome | Cushioned shoes or a heel cup, and no barefoot walking on tiles for now |
| The back of the heel, where the tendon meets the bone | Stiff and sore on the first steps and the first minutes of exercise. Tender on the back of the bone | Insertional Achilles tendinopathy | Calf loading on flat ground rather than off a step edge, and a small heel lift in the shoe for now |
| The back of the heel, a little higher, often with a bump | Swelling and tenderness just above where the tendon attaches. A hard bump that the shoe counter rubs | Retrocalcaneal bursitis, often with a Haglund’s deformity. See ankle bursitis | Shoes with a soft or open back, and calf loading. A doctor if it is hot and red |
| The back of the heel or low calf, after a sudden pop | A kick or a pop on a push-off. You cannot rise onto your toes on that leg alone | Achilles tendon rupture | The emergency department now |
| The whole heel, sore when squeezed from both sides | Gets worse with every step through the day rather than easing. Often after a jump in running or marching | Calcaneal stress fracture | Stop running and marching, and see a doctor |
| The inner heel and the sole | Burning, tingling, pins and needles or numbness. Sometimes pain at rest and at night | A trapped nerve: tarsal tunnel syndrome, or a small nerve under the heel called Baxter’s nerve | An assessment. A doctor if numbness spreads |
| The back or underside of the heel in a child | Usually aged about 8 to 14. Pain after sport, a limp, and a heel that hurts when squeezed | Sever’s disease, irritation of the growth plate at the back of the heel bone | A doctor first, to confirm it is the growth plate |
| Both heels at once | Morning stiffness in the back or other joints lasting more than half an hour, often in a younger adult | An inflammatory joint condition | A doctor, who decides on blood tests and a referral |
| Anywhere in the heel, not linked to standing or walking | Pain at night or at rest, fever, weight loss you cannot explain, a lump that grows | Rare causes, such as infection or a bone tumor | A doctor, soon |
If the pain sits under the ball of the foot instead, closer to the toes, that is metatarsalgia, a different problem again.
The other causes, in more detail
Achilles tendon problems. The pain is at the back of the heel, not underneath, where the cord at the back of your ankle meets the bone. Squeezing that cord is sore, and going up on tiptoe is often uncomfortable. Behind rather than below, look here first.
Calcaneal stress fracture. A small crack in the heel bone, usually from a sudden jump in running or marching load. Squeezing the heel from both sides at once hurts, which plantar fasciitis does not. It also behaves the opposite way, getting worse with every step rather than easing after the first few minutes.
Nerve entrapment. A small nerve runs close to the inside of the heel, and when irritated the pain changes character. Burning. Tingling. Sometimes numbness, sometimes pain at rest and at night. Burning rather than stabbing needs a look. The page on tarsal tunnel syndrome covers the nerve on the inside of the ankle.
Pain in the back of the heel when you stand
Pain at the back of the heel is a different family from pain underneath. The usual pattern is stiffness on the first steps in the morning, a sore spot on the back of the bone when you press it, and a shoe counter that rubs. When the tendon itself is sore where it attaches, it is insertional Achilles tendinopathy. When the sore spot is a little higher, with swelling on both sides of the tendon, a bursa between the tendon and the bone is often involved, sometimes over a bony bump called a Haglund’s deformity. Stretching the calf hard off the edge of a step often aggravates both, because it presses the tendon into the bone. A sudden pop at the back of the heel is different again, and it goes to the emergency department.
Pain in both heels
Both heels hurting at once is common in people who stand all day, and on its own it does not mean arthritis. It points to a doctor first when it comes with morning stiffness in the back or other joints lasting more than half an hour, swollen joints elsewhere, eye inflammation, or psoriasis. Those can belong to an inflammatory condition where the tendons and fascia become inflamed where they attach to bone, and that is diagnosed and treated by a doctor, often with a rheumatologist.
Is heel pain a sign of cancer?
Rarely. Almost all heel pain comes from a tendon, the plantar fascia, the fat pad, a nerve or bone that has been overloaded. Tumors of the heel bone are uncommon. The features that send you to a doctor instead of a physiotherapist are pain at night or at rest that has nothing to do with standing or walking, a lump or swelling that keeps growing, fever, weight loss you cannot explain, or a past history of cancer. With any of those, see a doctor soon rather than waiting it out.
Plantar heel pain: the first steps out of bed
Your alarm goes. You swing your legs off the bed, put your foot down, and something under your heel stabs. Sharp. Right in the middle of the underside, slightly towards the inside edge.
So you hobble. Short steps, weight on the outside of the foot, holding the wall to the bathroom. It eases off. Then you sit through a two hour meeting, stand up, and it is back. Same stab. Same twenty steps.
That pain in the heel is almost certainly coming from the plantar fascia, the thick band of tissue running along the sole of your foot. Our physios at Phoenix Rehab see more of this than almost any other foot problem.
Here is the honest part first. This one is slow. It is also, for most people, very treatable. The people who do well accept both.
What plantar fasciitis actually is
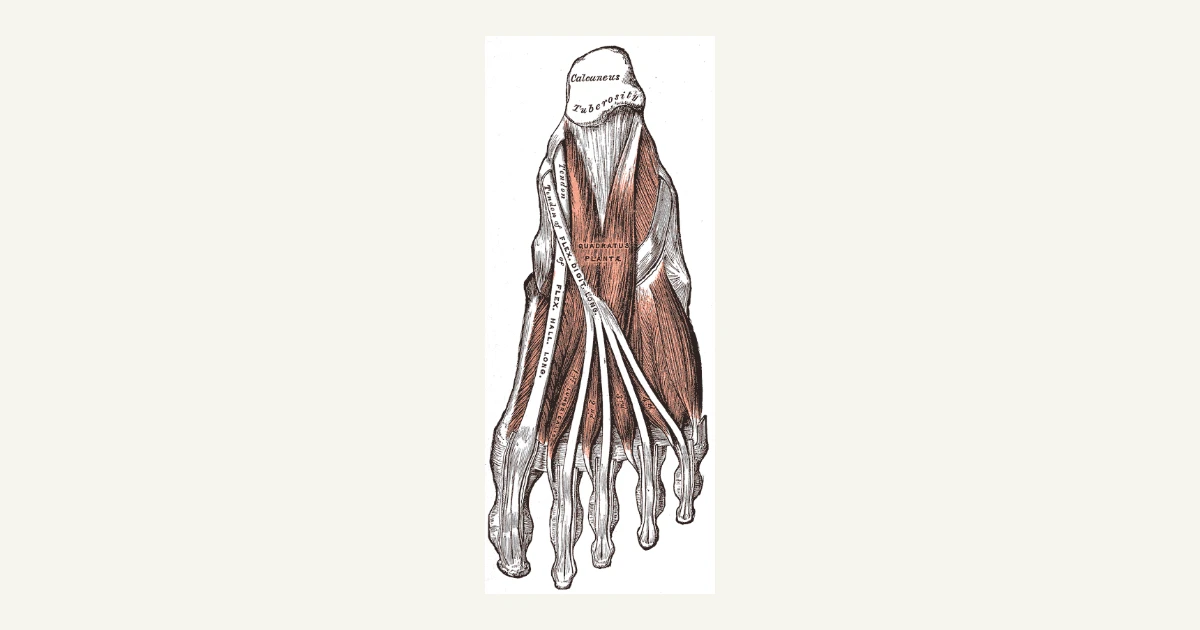
Run your thumb firmly along the sole of your foot, from the front of your heel bone towards your toes. Under the skin and the fat is a thick sheet of fibrous tissue. That is the plantar fascia.
It anchors into the underside of your heel bone, fans out across the sole, and attaches near the base of each toe. Think of your foot as a bow, the arch as the curve, the fascia as the bowstring pulled tight underneath. Every time you put weight through that foot the arch tries to flatten, and the fascia holds it together.
When the demand outruns what the tissue can handle, the fibers near the heel attachment change. They thicken and lose their neat organization. They become sensitive. Pressing that exact spot reproduces your pain almost every time, which is the most useful finding in an examination.
Heel inflammation, and the name
Plantar fasciitis ends in “itis”, which normally means inflammation. That is why the first thing anyone reaches for is an anti-inflammatory.
The tissue tells a different story. In long standing cases, what shows up looks less like classic inflammation and more like degeneration and overload. The fibers are disorganized rather than angry. Some clinicians now prefer plantar fasciopathy, or plantar heel pain.
This is not word games. If the tissue is overloaded rather than inflamed, calming inflammation alone will disappoint you, which is what most people find. And loading the tissue properly starts to make sense as treatment rather than something to avoid.
Why the first steps hurt, then ease, then come back
Overnight your foot rests with the toes pointed, and the plantar fascia settles into a shortened position. The first steps out of bed stretch it suddenly, and the sensitive tissue at the heel attachment objects. After a few minutes of walking it has adapted again and the pain eases. Sitting through a meeting, a drive or a movie does the same thing on a smaller scale, which is why the first steps after sitting hurt too.
The pattern matters more than the pain. Plantar fasciitis has a signature specific enough that you can usually tell within a minute whether your heel fits.
- Sharp or stabbing pain under the heel, worst on the first few steps after getting out of bed
- It eases within five to fifteen minutes of walking around
- It returns after sitting still, after driving, after a long meeting
- It worsens again late in the day if you have been on your feet a lot
- Pressing the inside front corner of the underside of your heel is tender, sometimes sharply so
- Pulling your toes back towards your shin makes that spot feel tighter and often more sore
- Walking barefoot on hard tiles is worse than walking in cushioned shoes
Rest settles it temporarily and does nothing for the capacity of the tissue, which is why it comes straight back.
Heel fat pad syndrome: the bruise that is not plantar fasciitis
The pad of fat under your heel is the shock absorber you land on with every step. It can be bruised by a hard landing, and it thins with age and after steroid injections into the heel. When it is the problem, the pain is a deep bruise in the middle of the heel, not a sharp pull at the front inner edge.a
| Heel fat pad | Plantar fasciitis | |
|---|---|---|
| Where it hurts | The middle of the heel, under the bone | The front inner edge of the heel, where the arch begins |
| When it is worst | Standing and walking on hard floors, barefoot, and later in the day | The first steps out of bed, and after sitting |
| Pressing on it | Tender in the center, like a bruise | Tender at the front edge; stretching the toes up often reproduces it |
| What usually helps first | Cushioned shoes or a heel cup, and no barefoot walking on tiles for now | A loading program for the fascia and calf |
The two often come together. Fat pad pain from a bruise usually settles over weeks once the heel is cushioned. Thinning from age does not come back, so the cushioning becomes part of how you buy shoes. If the pain followed a fall from a height, or you cannot put weight on the heel, see a doctor the same day.
Source: a. Yi TI, Lee GE, Seo IS, Huh WS, Yoon TH, Kim BR. Clinical characteristics of the causes of plantar heel pain. Ann Rehabil Med. 2011;35(4):507-513.
The heel spur myth
Our physios have this conversation almost every week. Someone arrives with an X-ray report and a sentence they have carried for months. There is a spur. They have pictured it ever since as a bone spike stabbing into their foot with every step. That is not what is happening, and letting go of that picture usually changes the whole recovery.
A heel spur is a small growth of bone extending forward from the underside of the heel bone. Spurs are common in people with no heel pain at all. Where a spur and pain occur together, the spur is generally understood as a consequence of long term traction rather than the cause. Removing it is rarely the answer, because heel pain routinely settles completely while the spur stays where it is.
Nobody did anything wrong by telling you about the spur. It is genuinely there on the film, and reporting what is visible is right. The spur is a finding, not an explanation. Your symptoms come from the tissue, and tissue responds to treatment.
Whether you need an X-ray or a scan at all is a decision for your doctor. Doctors usually think about imaging when the story does not fit plantar heel pain, after a fall or a hard landing, when a stress fracture is suspected, or when the heel has not responded to proper rehabilitation.
What causes plantar heel pain
Almost always a mismatch. The tissue was handling what you asked of it, then the ask went up or the capacity went down.
Sudden increases in load. A new running program. A 10K signed up for after two years off. A holiday spent walking twenty thousand steps a day. A new job on your feet for nine hours instead of sitting.
Standing work on hard surfaces. Retail floors, hawker stalls, kitchens, wards, security posts. Standing mostly still on unforgiving ground is harder on the fascia than walking is.
Weight changes. Gaining weight loads the arch harder with every step, and so does pregnancy. Physics, not a judgment.
Tight or weak calves. Your calf and Achilles connect to the back of your heel bone, and the plantar fascia connects to the underside. A tight calf pulls the heel upwards at the back, and the fascia takes more strain at the front. This is why calf work sits at the center of treatment.
Footwear and foot shape. Flat, unsupportive shoes give the arch nothing to work with, and worn out running shoes do the same. Very flat feet and very high rigid arches load the fascia differently, though neither makes the problem certain.
Heel pain from long standing
Long standing is the cause we hear most often in Singapore. A shift on the shop floor at a mall. Eight hours behind an F&B counter. A twelve hour nursing shift on ward floors. Guard duty, parade practice and route marches in NS. Standing still loads the heel without the short rest that walking gives each foot between steps, so the ache builds through the shift and the first steps after the break are the worst. Both heels often hurt in standing jobs.
The fix is rarely to stop working. It is usually a shoe with a cushioned heel and a firm midsole for the shift, a short walk or a calf raise set at each break so you are not standing in one spot, and a loading program built around your roster.
The Singapore part
Flip flops and slides are daily footwear here, not holiday footwear. Flat, thin, and your toes grip slightly to keep them on. Hours of that is a genuine contributor, and our physios see it constantly in people who believed their footwear was neutral.
Home floors are tiled, and most of us are barefoot on them from the moment we get home until bed. That is often the biggest block of unsupported standing in the day. Retail, service and hawker work adds long hours on concrete, and a Saturday on the marble at Orchard is several kilometers with no give at all. Long runs on concrete pavements in this heat count too.
What we test at the first appointment
The first appointment starts with sorting out what is actually causing your pain in the heel. Our physios ask about your morning pattern, your working day on your feet, what changed in the weeks before it started, and what you have already tried. Then they examine the foot.
- Where it is tender. Pressing the front inner edge of the heel, the middle of the fat pad, the back of the heel bone and the Achilles, and squeezing the heel from both sides. These are the spots that separate fascia from fat pad from tendon from bone.
- Calf length, two ways. The knee-to-wall lunge with the knee bent, and the calf with the knee straight, each measured against the other leg.
- Single-leg heel raises, counted. As many as you can do at a set pace on each leg. The sore side is usually several short of the other.
- The windlass test. Standing, the big toe is lifted back. If that reproduces your heel pain, the plantar fascia is involved.
- The nerve. Tapping along the inside of the ankle and heel, and checking feeling on the sole, when the pain burns or tingles.
- How you walk and stand. Watching you walk, and what your foot does when you stand on one leg.
From there you get a plan you can actually run. The loading program set at the level your tissue handles now, footwear guidance for your working day, and a timeline so you know whether you are on track at week four instead of guessing. If the test points somewhere a physiotherapist should not go alone, such as a possible stress fracture, a nerve that is getting worse, or both heels with stiff joints elsewhere, we tell you and write to your doctor.
What usually helps plantar heel pain
Plantar fasciitis treatment, ordered from least to most invasive. Most people never get past the first three. The 2023 clinical practice guideline for physical therapists on plantar heel pain supports the same core: load management, calf and plantar fascia stretching, footwear and insoles, and taping in the short term.1
Load management. Not rest. Rest alone costs you fitness and gives back nothing. Bring the daily load under the level that keeps flaring it while you build the tissue up. Cut the long standing blocks, wear supportive shoes indoors instead of going barefoot on tiles, and keep fitness through cycling or swimming.
Stretching. Calf and plantar fascia stretching eases symptoms quickly, especially that first morning step. Worth doing, and on its own incomplete. Stretching alone is the most common thing we see people doing for months without progress.
Progressive loading of the fascia. Almost everyone arrives having stretched and rested. Far fewer arrive having loaded the fascia, and this is the part that matters most. Strong, slow, heavy loading, through heel raises with the toes held in an extended position, appears to produce better outcomes than stretching alone. It gives the fascia a reason to remodel and rebuild capacity rather than simply being told to calm down. In a 2015 trial, people with plantar fasciitis who did slow single-leg heel raises with a towel rolled under the toes, every second day, alongside insoles, scored better at three months than people who stretched daily alongside insoles. By twelve months the two groups were similar.2 The program is in the next section.
Footwear and arch support. Shoes with a cushioned heel and a firm midsole reduce strain through the fascia. Over the counter arch supports help a meaningful number of people within weeks, and custom insoles are an option where foot shape calls for it. Support lowers load while the tissue recovers. It does not build capacity, so it sits alongside the loading work, never instead of it.
Taping. A supportive tape job under the arch settles symptoms quickly. A short term tool for getting through a working week, not the treatment itself.
Night splints. A brace holding the ankle at ninety degrees while you sleep, so the fascia does not rest all night shortened. It targets exactly that first morning step. Plenty of people cannot sleep in one. If you can, it is worth trying for stubborn heel pain in the morning.
Injections. Whether to have an injection is a decision for your doctor, not your physiotherapist. If your doctor has offered an injection, or you have had one, see physiotherapy after an injection.
Shockwave therapy. An option for cases that have not responded to several months of good rehabilitation. Not a first line answer.
Surgery. Rare, and a last resort after a genuine trial of everything else.
What physiotherapy actually adds is the assessment first. Whether this is fascia, fat pad, nerve or bone changes the entire plan, and that is worth more than any single technique. After that it is a loading program matched to your real capacity, and someone keeping you on it through the months where nothing appears to be changing.
Can I keep running with heel pain?
Often yes, at reduced volume, if the pain settles within 24 hours and is not worse the following morning. Cut the distance, drop hills and speed work, and run on softer ground rather than concrete where you can. If your first steps the next day are noticeably worse, that run was too much. The running injuries guide covers the rest of the foot and leg.
Exercises and what to do at home
These are general. Get assessed first, particularly if your pattern does not match the picture above, because the wrong exercises for a stress fracture or a nerve problem waste months.
1. Plantar fascia stretch, before your first step. Sit on the edge of the bed. Cross the sore foot over the opposite knee. Pull your toes back towards your shin until the band along your sole goes tight. Hold 10 seconds, 10 repetitions. Do this before your feet touch the floor, and again before standing after any long sit. For morning pain, this is the highest value thing on the list.
2. Calf stretch, knee straight then knee bent. Hands on a wall, sore leg back, heel flat. First with the back knee locked straight, leaning forward until you feel it in the upper calf. Then the same position with the back knee slightly bent, which drops the stretch lower towards the ankle. Hold 30 seconds, 3 repetitions each. Both are needed because they reach different muscles, and the deeper one attaches nearer the heel where your problem sits.
3. Rolling the sole. Freeze a small water bottle and roll it under your arch with moderate pressure for 5 minutes at the end of the day. This is for comfort. It builds nothing, so do not let it replace the next one.
4. The progressive heel raise loading program. This is the one that changes things. Stand with the ball of the sore foot on a step, heel hanging off the back. Roll a towel under your toes so they are bent upwards while you stand. That toe position pulls the fascia tight and puts the load where you want it.
What our patients say
Google reviews from our clinics in Singapore.


Rise slowly onto the ball of the foot over 3 seconds. Hold 2 seconds. Lower over 3 seconds. The tempo is not optional, because the slowness is what makes the load count.
Start on both feet, 12 repetitions, 3 sets, every second day. When that feels comfortable, shift more weight onto the sore side, then single leg, then add load in a backpack.
The progression rule. Pain during the exercise up to about 4 out of 10 is acceptable. What matters is the next morning. If your first steps are worse, hold at the level you were at. Same or better, you are ready to add.
If the pain is at the back of the heel rather than underneath, do the heel raises on flat ground, not off the step, until someone has looked at it.
Is this normal?
Usually expected: the first steps out of bed are the worst and ease within minutes. The pain comes back after sitting. The heel aches after a long day on your feet and is better again by the next morning. The morning pain improves before the end of shift ache does. Some soreness during the heel raises that has settled by the next morning.
Worth getting checked: heel pain that is the same or worse after six weeks of sensible self-management. Pain that builds with every step instead of easing. Burning, tingling or numbness. Both heels, with stiffness in the back or other joints. A child with heel pain and a limp.
How long does heel pain take to settle?
The gap between expectation and reality is what makes people quit. These are typical ranges, and your own doctor’s or physiotherapist’s plan for your heel comes first.
| What | Typical range |
|---|---|
| The first steps out of bed start to ease | Often within 4 to 8 weeks of changing the load and starting the loading work |
| A bruised fat pad | Usually settles over weeks once the heel is cushioned |
| Plantar heel pain that has been going on a while | Three to twelve months is realistic |
| Keeping the loading going | At least three months past the point where you feel better |
Here is the most useful sentence on this page. The single biggest reason heel pain drags on for years is that people stop the loading program as soon as the morning pain eases.
The morning pain settles first, well before the tissue has rebuilt its capacity. So around week six or eight, when you can reach the bathroom without holding the wall, stopping feels reasonable. Then comes a heavy week at work, it returns, and you decide the exercises did not work.
They did work. They were stopped at halfway. Keep the loading going for at least three months past the point where you feel better.
Recovery is slower when the pain has been there over a year, when the standing load cannot be reduced, when calf tightness is not addressed, and when footwear does not change. In one study that followed 174 people referred to a hospital clinic with plantar fasciitis, about half still had symptoms five years after they started.3 Those were people whose heels had already been stubborn enough to reach a hospital, so it is not the usual course. It is the reason the loading work is worth finishing.
When to see a doctor first
Most heel pain is not sinister. Some is.
- Call 995 after a fall from a height onto your heels if you have back or neck pain, or numbness or weakness in the legs. Do not get up and walk.
- Go to the emergency department now if, after a fall from a height or a hard landing on your heels, you cannot take weight on the foot or the heel is badly swollen. Also if you felt a pop or a kick at the back of the heel or low in the calf and now cannot rise onto your toes on that leg alone. Also for a heel or foot that is hot, red and swollen with a fever, or that is hot, red and swollen in someone with diabetes.
- See a doctor the same day for heel pain after a fall or a jump when you can stand on it but squeezing the heel hurts. Also for a heel that is hot, red or swollen without a fever, or a wound or blister on the heel in someone with diabetes or reduced feeling in the feet.
- See a doctor soon for pain that gets worse with every step through the day rather than easing. Also for numbness, burning or pins and needles that is spreading or is in both feet, especially with diabetes. Also for pain in both heels with morning stiffness in the back or other joints lasting more than half an hour, pain at night or at rest, weight loss you cannot explain, a lump that grows, or a child with heel pain and a limp.
Beyond those, the signal is trajectory, not intensity. Heel pain slowly improving over four to six weeks of sensible self-management is on the right road. Heel pain that is the same or worse after six weeks is the point to get assessed, rather than to try a fourth pair of insoles.
Heel pain: who does what
- A doctor (your GP, a polyclinic doctor, a sports doctor or the emergency department) examines the heel, decides whether you need an X-ray, an ultrasound, an MRI or blood tests, decides about medication and injections, and refers you to a surgeon or a rheumatologist when it is needed.
- An orthopedic or foot and ankle surgeon sees the Achilles rupture, the heel fracture and the rare heel that needs an operation.
- A physiotherapist works out which structure is sore, measures the calf and the heel raises against the other leg, treats the stiffness and the pain, tapes when it helps, and loads the heel back in stages to a full shift, a long walk or a run. Pain relief and anti-inflammatory medication are a decision for your doctor or pharmacist.
The four stages, applied to a heel
In the Phoenix Recovery Protocol the work starts at Calm & Protect: shoes on the tiles, the long standing blocks cut, taping for the working week, and the stretch before the first step. Move & Mobilize takes the calf length back toward the other side, with the knee straight and the knee bent. Rebuild & Strengthen is the heel raise program, from two legs to one, then with load. Return & Perform tests the tasks themselves: the full shift, the long walk, the run. The measures set the pace.
Frequently asked questions
What causes heel pain?
The most common cause is plantar fasciitis, felt as sharp pain under the heel on the first steps out of bed. Pain at the back of the heel usually comes from the Achilles tendon where it joins the bone. Other causes include a bruised or thinned fat pad, a stress fracture, a trapped nerve and inflammatory joint conditions.
Why does my heel hurt most in the morning?
Overnight your foot rests with the toes pointed, and the plantar fascia settles into a shortened position. The first steps out of bed stretch it suddenly, and the sensitive tissue at the heel attachment objects. After a few minutes of walking it has adapted again and the pain eases. Stretching the fascia before your first step makes a real difference.
What causes pain in the back of the heel?
Pain at the back of the heel usually comes from the Achilles tendon where it attaches to the heel bone, called insertional Achilles tendinopathy, or an irritated bursa above it, sometimes over a bony bump called a Haglund’s deformity. A sudden pop at the back of the heel, with no tiptoe on that leg alone, needs the emergency department.
Why do both of my heels hurt?
Both heels often hurt together in people who stand all day, and on its own that does not mean arthritis. See a doctor first if it comes with morning stiffness in the back or other joints lasting more than half an hour, swollen joints elsewhere, or psoriasis, because those can point to an inflammatory condition.
Is heel pain a sign of cancer?
Rarely. Almost all heel pain comes from a tendon, the plantar fascia, the fat pad, a nerve or bone that has been overloaded. See a doctor soon if the pain comes at night or at rest and has nothing to do with standing, if a lump keeps growing, or with fever, unexplained weight loss or a past history of cancer.
Had an injection?
The heel injection worked. The first steps out of bed are coming back.
Whether to have an injection, and whether to have another, is a decision for your doctor. If your doctor has offered one, or you have had one, the work for the heel is the same as without it: calf and plantar fascia loading, and footwear, because those change how the heel copes with a day on your feet.
Where are you with this right now?
1. It is settling on its own
Foot and ankle problems are slow but usually very treatable. Months rather than weeks is normal, and improvement is judged over a month, not a day. If the first steps in the morning are easier than they were four weeks ago, you are on the right road. Keep the shoes on at home, keep the stretch before the first step, and keep the heel raises going for three months past feeling better. You do not need us for this, and we would rather say so.
2. It has stopped improving
6am. You sit on the edge of the bed and do the stretch first, because you know what the floor feels like. Then the first ten steps to the bathroom, holding the wall. Four months of this.
On the MRT platform you shift from foot to foot until the train comes. At work you stand through the shift on the shop floor, the ward or the counter, and by the afternoon you are counting the hours to the break. You have stopped walking to the MRT and take a Grab. The weekend run went first, then badminton.
Rest and new shoes were supposed to fix it. You rested. You bought the shoes, then the insoles, then another pair. In your own weeks since, the first steps out of bed have not changed.
The morning pain is what everyone asks about. Has anyone counted your heel raises against the other side?
The half marathon in March, the IPPT window, or a roster that does not get shorter. Whichever is yours, it is a date your heel has to meet.
Symptoms settle well before the tissue has rebuilt its capacity, which is why stopping the loading work early is the most common reason this drags on for years. That is the gap worth measuring, and it is not measured by how you feel on the day.
If anything on this page sent you to a doctor first, go there first. If a doctor has ruled those out, or you never needed one, the Stalled Recovery Review is three appointments over three weeks with the same physiotherapist. The first finds what is limiting the heel: the tender spot, the calf length and the heel raises, counted on both sides. The next two measure how it responds. $690, nett, no GST, which is three appointments at $230.
3. You have had an injection or an operation
After an injection, see physiotherapy after an injection. The loading work is the same, and your doctor decides on the injection.
After an operation on the heel, the Achilles or the plantar fascia, or a heel fracture, recovery has a shape, and knowing which stage you are in tells you whether you are on it. See physiotherapy after surgery, the Achilles Rupture Recovery Program, foot fracture physiotherapy, or the recovery programs. Your surgeon’s protocol takes precedence.
All of it runs on the same four stages. The Phoenix Recovery Protocol explains what each stage works on and what you have to meet to move up. No referral needed to start.
Next step
Find out which stage you are in
Still holding the wall on the first steps out of bed, weeks after the new shoes. One Assessment and Treatment is a single 45-minute appointment at $230, nett, no GST. Your therapist finds what is actually causing the heel pain, counts your heel raises against the other side, treats what is limiting you in the same appointment, and you leave with your current stage and a written plan.
Phoebe replies with a clinic and two times. Bring the shoes you wear most, your insoles, and any X-ray or scan report. Prefer to phone? Each of our five clinics has its own number on the clinics page. No referral needed to book.
Related reading
Sources: 1. Koc TA Jr, Bise CG, Neville C, Carreira D, Martin RL, McDonough CM. Heel pain, plantar fasciitis: revision 2023. J Orthop Sports Phys Ther. 2023;53(12):CPG1-CPG39. 2. Rathleff MS, Molgaard CM, Fredberg U, Kaalund S, Andersen KB, Jensen TT, Aaskov S, Olesen JL. High-load strength training improves outcome in patients with plantar fasciitis: a randomized controlled trial with 12-month follow-up. Scand J Med Sci Sports. 2015;25(3):e292-e300. 3. Hansen L, Krogh TP, Ellingsen T, Bolvig L, Fredberg U. Long-term prognosis of plantar fasciitis: a 5- to 15-year follow-up study of 174 patients with ultrasound examination. Orthop J Sports Med. 2018;6(3):2325967118757983.
Where we are
Clinics across Singapore
ORCHARD
400 Orchard Road #12-12
Orchard Towers, S238875
NS22 Orchard MRT
Physiotherapy and hand therapy in Orchard →
WhatsApp 8800 1830TAMPINES
9 Tampines Grande #01-20
Asia Green, S528735
EW2DT32 Tampines MRT
Physiotherapy and hand therapy in Tampines →
WhatsApp 8780 9608SERANGOON
265 Serangoon Central Drive #04-269
S550265 · Lift C only
NE12CC13 Serangoon MRT
Physiotherapy and hand therapy in Serangoon →
WhatsApp 8892 4121TANJONG PAGAR
10 Anson Road #02-77A
International Plaza, S079903
EW15 Tanjong Pagar MRT
Physiotherapy and hand therapy in Tanjong Pagar →
WhatsApp 8227 7074JURONG EAST
2 Venture Drive #02-02
Vision Exchange, S608526
NS1EW24 Jurong East MRT
Opening 25 October 2026
Physiotherapy and hand therapy in Jurong East →
WhatsApp 8242 7340